

If your breast cancer has been described as HER2-negative, it may in fact be HER2-low, and that can open up a treatment option you might not know about. Around half of all breast cancers are HER2-low. This guide is for anyone living with breast cancer, and especially secondary (metastatic) breast cancer, who wants to understand what HER2-low means, how it is tested, and whether trastuzumab deruxtecan (Enhertu®), now recommended by NICE for routine NHS use in England, could be an option for them.
Key takeaways
- HER2-low means the cancer cells have a small amount of the HER2 protein on their surface (an IHC score of 1+, or 2+ with a negative ISH test). Around half of breast cancers are HER2-low, and most of these are also hormone receptor-positive (HR+).
- Being HER2-low does not currently change the treatment offered for primary (early) breast cancer, but in secondary breast cancer it can make you eligible for Enhertu.
- In September 2026, NICE recommended Enhertu for routine NHS use in England for HER2-low secondary breast cancer after chemotherapy. It has been available in Scotland since 2023.
- In the DESTINY-Breast04 trial, the median time before the cancer grew or spread was 9.9 months on Enhertu compared with 5.1 months on chemotherapy, and median survival was 23.4 months compared with 16.8 months.
- Enhertu can cause inflammation of the lungs, so a new cough, breathlessness or fever should always be reported to your care team straight away.
- The OWise app lets you save your HER2 score and questions for your oncologist in one place, and track side effects day by day if you start Enhertu.
In this article
- What is HER2?
- How is HER2 status measured?
- How common is HER2-low breast cancer?
- What does being HER2-low mean for my treatment?
- Which treatments are approved for HER2-low breast cancer?
- What is trastuzumab deruxtecan (Enhertu®) and how does it work?
- What side effects can Enhertu cause?
- What did the DESTINY-Breast04 trial show?
- Have other HER2-targeted treatments been tested?
- HER2-low breast cancer summed up
- Questions to ask your care team
What is HER2?
HER2 (human epidermal growth factor receptor 2) is a protein on the surface of cells that helps control how they grow and divide. In HER2-positive (HER2+) breast cancer, the cancer cells have very large amounts of HER2 on their surface (this is called overexpression), which drives abnormal cell division and growth. HER2-low breast cancer cells also have HER2 on their surface, but much less of it.
Read our guide to HER2-positive breast cancer to learn more about the HER2-positive type.
How is HER2 status measured?
HER2 status is measured on a sample of the tumour, usually with an immunohistochemistry (IHC) test and, when the result is borderline, an in situ hybridisation (ISH) test.
The IHC test stains the cancer cells to show how much HER2 protein is on their surface and gives a score from 0 to 3+. If the IHC score is 2+, an ISH test, such as fluorescence in situ hybridisation (FISH), looks at the DNA of the cancer cells to see whether there are extra copies of the HER2 gene. ISH results are either positive or negative1.
Table 1. HER2 status: how IHC and ISH test results are used to describe HER2 status in breast cancer1,2.
| HER2 status | Test result |
|---|---|
| HER2-zero (also called HER2-null) | IHC 0 with no HER2 staining |
| HER2-ultralow | IHC 0 with faint staining in up to 1 in 10 cancer cells |
| HER2-low | IHC 1+, or IHC 2+ with a negative ISH (FISH) test |
| HER2-positive | IHC 3+, or IHC 2+ with a positive ISH (FISH) test |
HER2-zero, HER2-ultralow and HER2-low all sit within what has traditionally been called HER2-negative breast cancer. Many pathology reports simply say “HER2-negative”, so the IHC score is the number that tells you whether your cancer is HER2-low. You can find it on your pathology report.
HER2 status is not always fixed. It can differ between the original (primary) tumour and a secondary cancer, and because the amount of staining at the lower end is so small, pathologists do not always agree on whether a sample is IHC 0 or 1+1. If you have secondary breast cancer and an earlier result was IHC 0, it is worth asking your team whether a biopsy of the secondary cancer or a retest could be helpful.
How common is HER2-low breast cancer?
Around half of all breast cancers are HER2-low1 (figure 1).
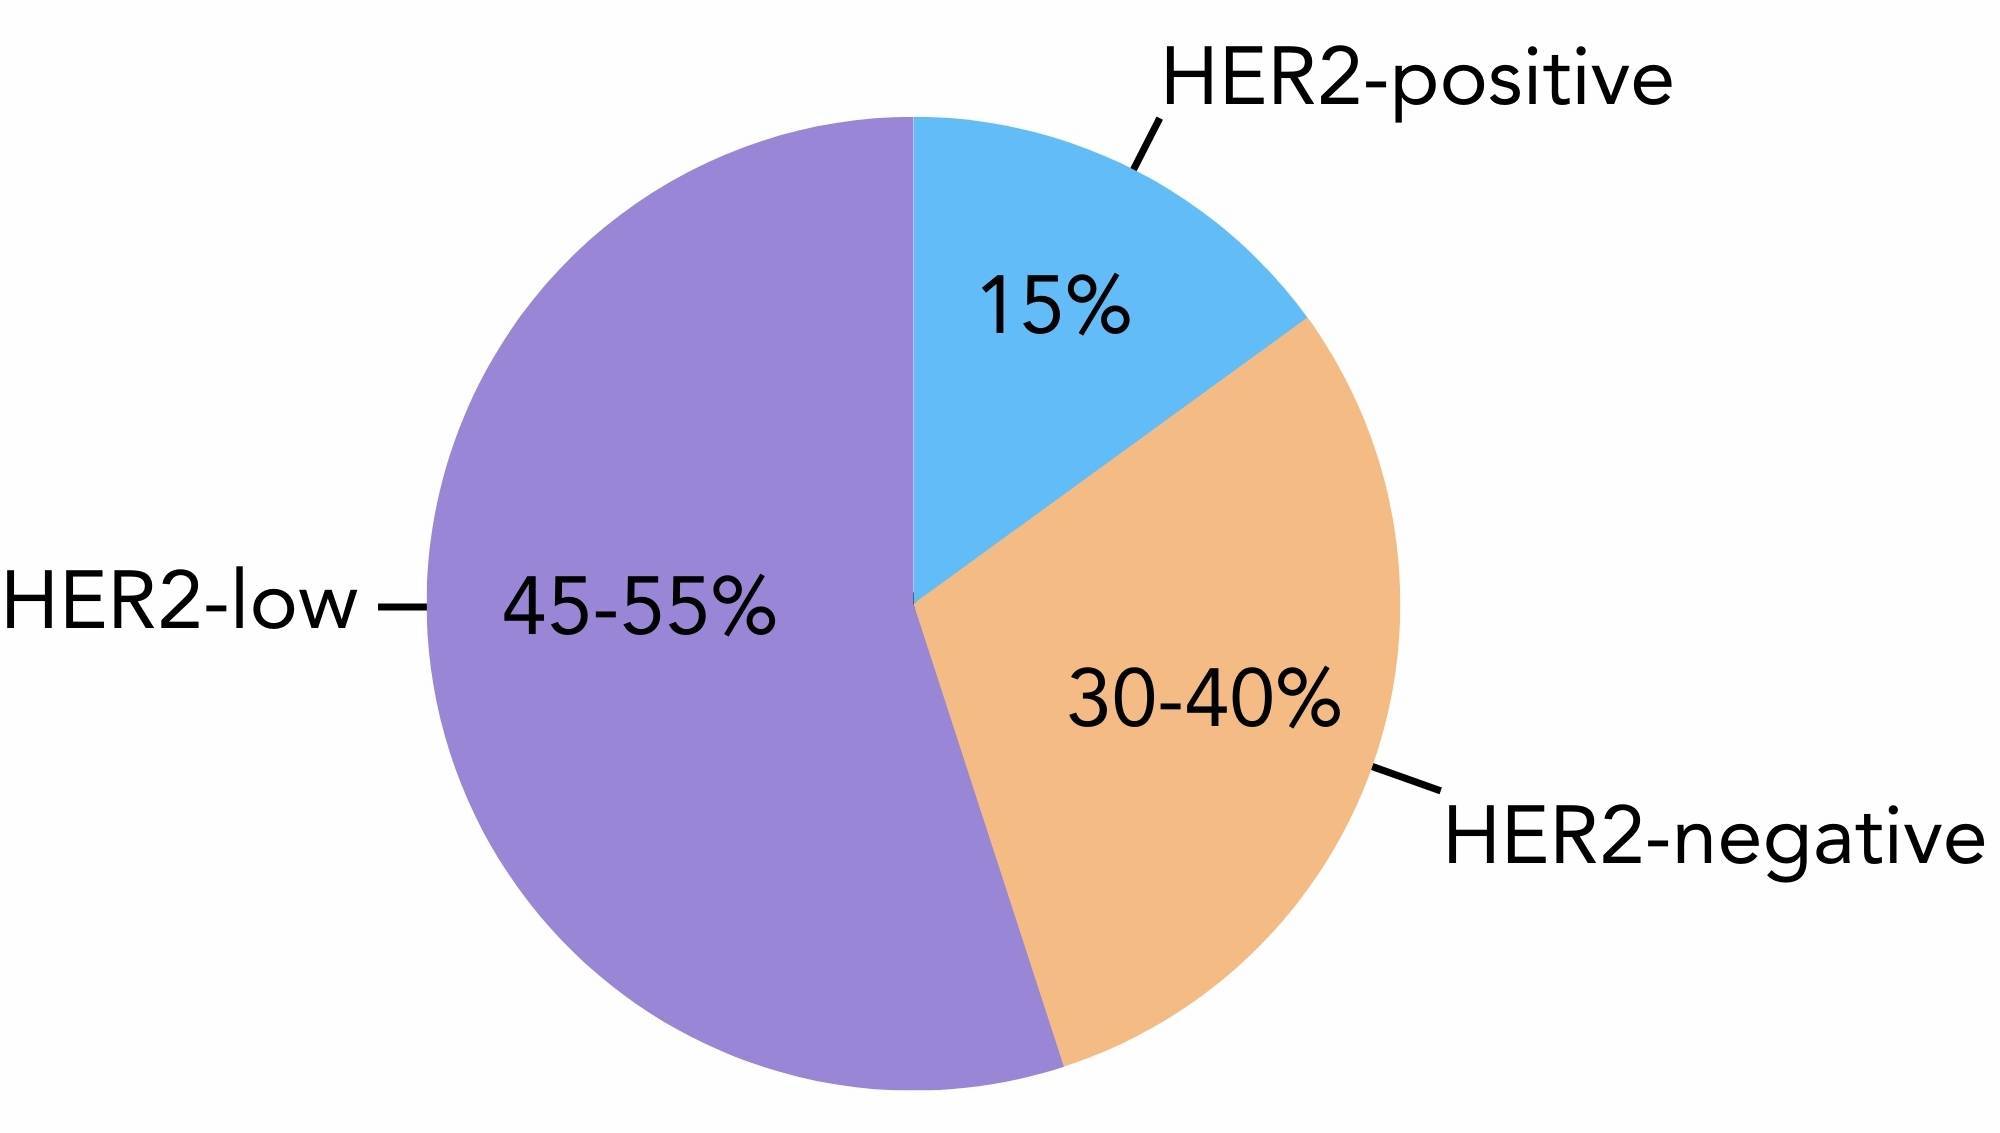
Figure 1. Approximate proportion of breast cancers that are HER2-positive (around 15%), HER2-low (around 45 to 55%) and HER2-negative with an IHC score of 0 (around 30 to 40%).
Most HER2-low breast cancers are also hormone receptor-positive (HR+). In a large UK study of more than 5,700 breast cancers from Nottingham, 9 in 10 HER2-low cancers were HR+3. HER2-low is less common in triple negative breast cancer (TNBC), but it does occur.
What does being HER2-low mean for my treatment?
If you have secondary breast cancer, being HER2-low can make you eligible for a HER2-targeted treatment called trastuzumab deruxtecan (Enhertu®).
Until recently, breast cancers were grouped as either HER2-positive or HER2-negative, and only HER2-positive cancers were treated with HER2-targeted drugs. Research has since shown that Enhertu can work when there is only a small amount of HER2 on the cancer cells, so the HER2-low group now matters for treatment decisions1,4.
At the moment, being HER2-low does not change the treatment offered for primary (early) breast cancer. It becomes important if the cancer has spread, when it can add Enhertu to the treatment options for both HR+ and triple negative secondary breast cancer.
“The takeaway from all this is that we have many new options. We have this new problem deciding what to use. We’ve never had this. All these choices are good to have because you can adapt treatment.” Paolo Tarantino, MD5
If you want to know your HER2 status, check your pathology report or ask your care team for your IHC score.
Not sure what your HER2 score is, or whether it has been retested since your cancer spread? Add questions such as “What is my HER2 IHC score?” and “Could I be HER2-low?” to a question list in the OWise app before your next appointment. You can choose from suggested questions or add your own, then record the answers with notes, photos or an audio recording, so you have the details to hand when you get home.
Which treatments are approved for HER2-low breast cancer?
Trastuzumab deruxtecan (Enhertu®) is approved to treat HER2-low secondary breast cancer in the UK, EU and US.
It is approved for adults whose HER2-low breast cancer has spread or cannot be removed with surgery, and who have already had chemotherapy for secondary breast cancer, or whose cancer came back during or within 6 months of finishing chemotherapy after surgery (adjuvant chemotherapy)6,7.
Table 2. Enhertu for secondary breast cancer: approval and NHS status by HER2 status (September 2026)2,6,7,8.
| HER2 status | Can Enhertu be used? |
|---|---|
| HER2-zero | Not a treatment option |
| HER2-ultralow | Approved in the US and EU for HR+ secondary breast cancer after hormone therapy. Not part of the current NICE recommendation in England. |
| HER2-low | Approved in the UK, EU and US after chemotherapy, and recommended by NICE for routine NHS use in England. Also approved in the US and EU for HR+ secondary breast cancer after hormone therapy. |
| HER2-positive | Approved |
Is Enhertu available on the NHS for HER2-low breast cancer?
Yes. On 17 September 2026, NICE published final draft guidance recommending Enhertu for routine NHS use in adults with HER2-low advanced or metastatic breast cancer whose disease has progressed after chemotherapy, and eligible people in England can now be offered it. Around 1,000 people are expected to benefit8.
This reverses NICE’s 2024 decision, when Enhertu was not recommended because it was not considered cost-effective at the price offered. The new recommendation followed a commercial agreement with the manufacturers and changes to the way NICE assesses value for money8.
In Scotland, Enhertu has been available for HER2-low secondary breast cancer since December 20239. Access in Wales and Northern Ireland follows separate processes, so if you live there, ask your care team what this means for you.
Can Enhertu be used before chemotherapy?
In the US and EU, yes, for some people with HR+ secondary breast cancer. The DESTINY-Breast06 trial included 866 people with HR+, HER2-low or HER2-ultralow secondary breast cancer whose cancer had grown despite hormone (endocrine) therapy and who had not yet had chemotherapy for secondary disease. In the HER2-low group, the median time before the cancer grew or spread was 13.2 months on Enhertu compared with 8.1 months on chemotherapy2.
Based on these results, Enhertu was approved for this earlier use in the US in January 2025 and in the EU in April 2025, including for HER2-ultralow cancers10,11. The current NICE recommendation covers use after chemotherapy only, so this earlier use is not part of routine NHS care in England at present.
What is trastuzumab deruxtecan (Enhertu®) and how does it work?
Trastuzumab deruxtecan (Enhertu®) is an antibody-drug conjugate (ADC): a monoclonal antibody and a chemotherapy drug joined together by a chemical linker12.
What are antibody-drug conjugates?
Antibody-drug conjugates deliver chemotherapy directly to cancer cells. Monoclonal antibodies (also called mAbs) are proteins made in the lab that can bind to specific targets (antigens) on the surface of cells13. Chemotherapy uses anti-cancer drugs to interfere with how cancer cells grow and divide. It targets fast-dividing cells in general, which means it can damage healthy cells as well as cancer cells14. ADCs use the antibody to find cancer cells carrying a particular antigen and deliver the chemotherapy drug straight to them, which is designed to reduce the effect on healthy cells12,15. Trastuzumab deruxtecan is made up of the monoclonal antibody trastuzumab linked to the chemotherapy drug deruxtecan (figure 2).
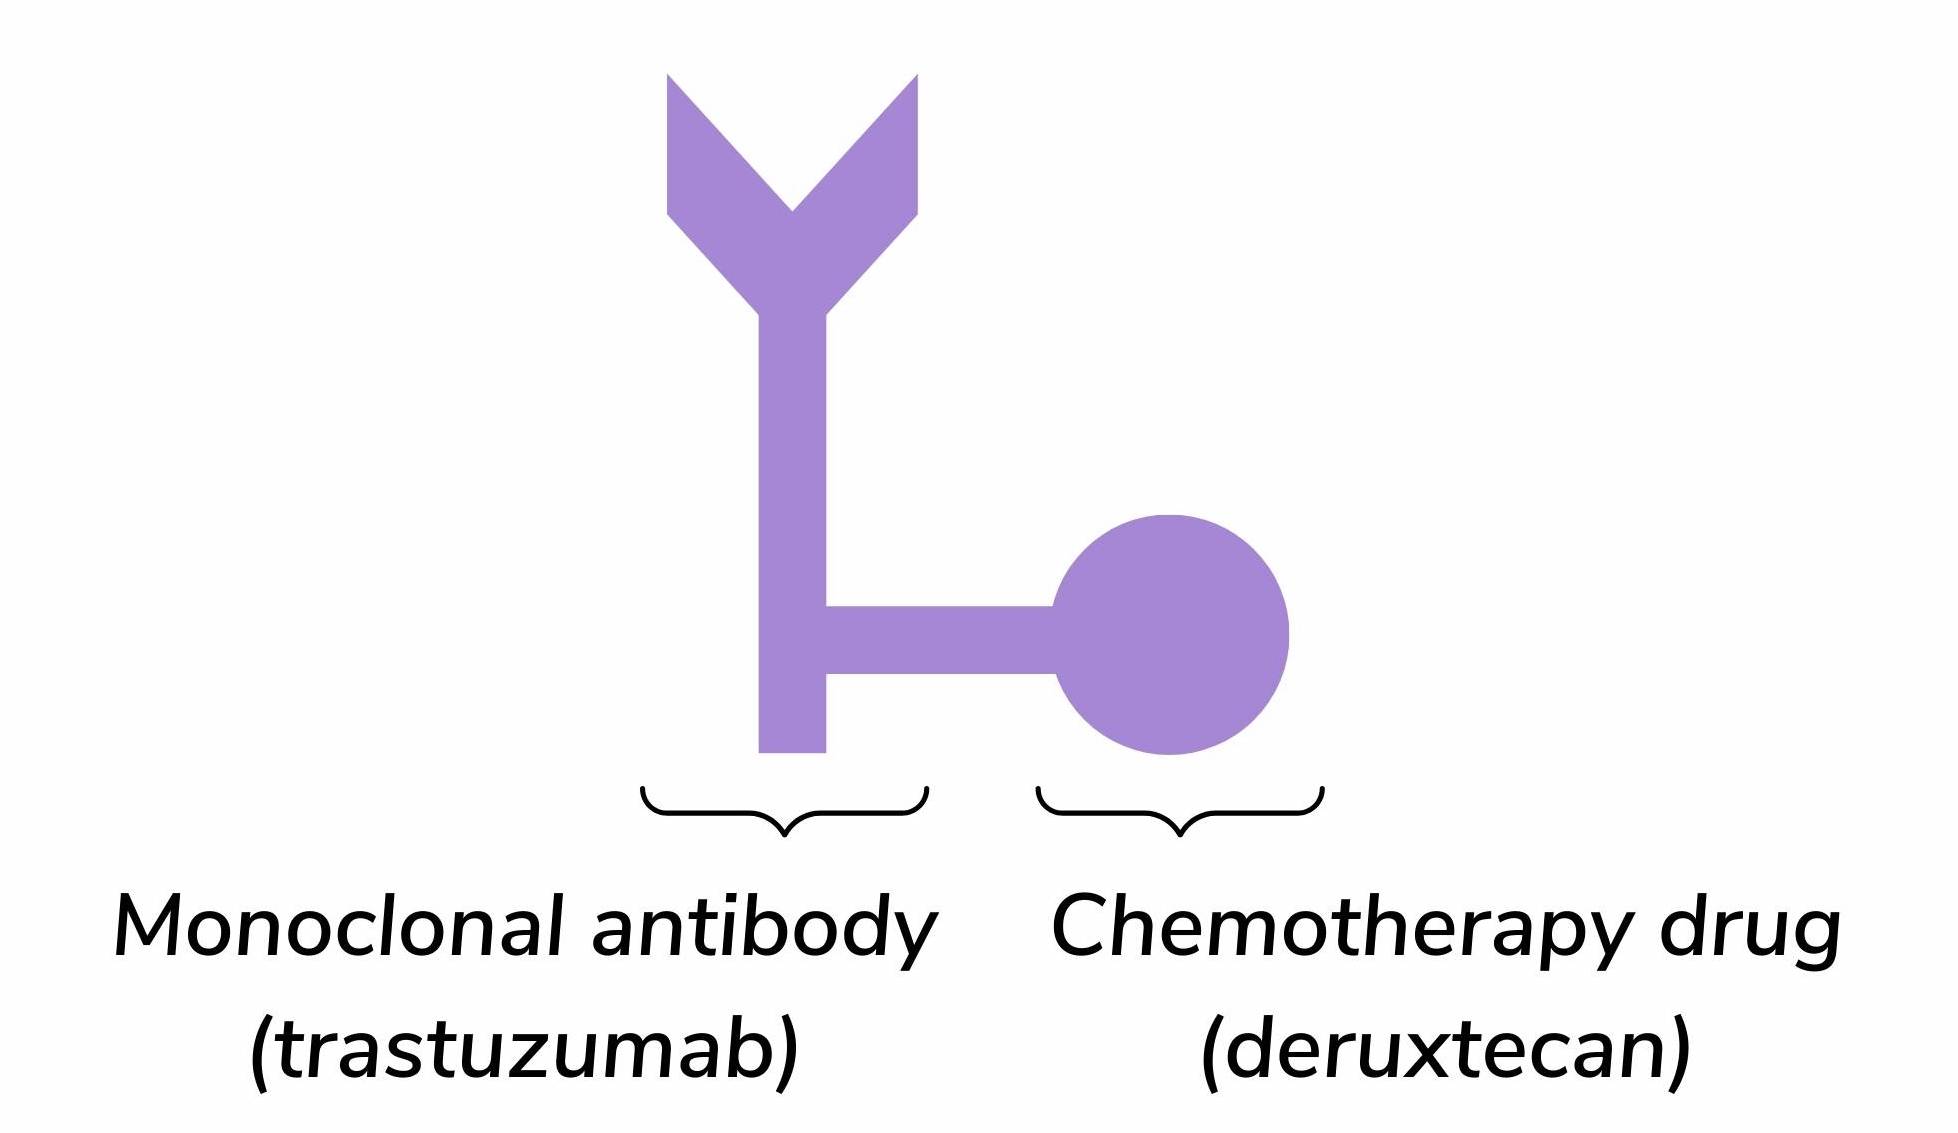
Figure 2. The structure of trastuzumab deruxtecan (Enhertu®).
How does Enhertu work in HER2-low breast cancer?
The antibody part of Enhertu attaches to HER2 on cancer cells and carries the chemotherapy drug inside them. Once Enhertu has been taken into the cell, enzymes split the linker and release deruxtecan. Deruxtecan damages the DNA of the cancer cell so that it can no longer grow and divide, and the cell dies16,17.
Two features help explain why Enhertu can work when there is only a little HER2. Each antibody carries a large amount of chemotherapy (around eight drug molecules), and once released, deruxtecan can pass into neighbouring cancer cells, including cells with little or no HER2. This is known as the bystander effect16,17. Trastuzumab on its own (Herceptin®) needs large amounts of HER2 to work, which is why it has not helped people with HER2-low breast cancer (see below).
What side effects can Enhertu cause?
The most common side effects of Enhertu are feeling sick, tiredness and hair loss, and it can sometimes cause serious inflammation of the lungs.
In the DESTINY-Breast04 trial, around 7 in 10 people who had Enhertu experienced nausea, and tiredness, vomiting, hair loss and low blood cell counts were also common4. Anti-sickness medicine can help, and your team may pause treatment or lower the dose if side effects become difficult.
Enhertu can cause inflammation of the lungs (interstitial lung disease or pneumonitis). In DESTINY-Breast04 this affected around 1 in 8 people (12%) who had Enhertu. Most cases were mild or moderate, but it can be serious and, rarely, life-threatening4. Contact your care team straight away if you develop a new or worsening cough, shortness of breath or a high temperature.
Starting Enhertu and wondering whether a new symptom is worth mentioning? Log nausea, tiredness, breathlessness or a cough each day in the OWise app. A clear record of when each symptom started and how it has changed helps your care team spot problems early and decide whether your dose needs adjusting. Breathing changes should always be reported to your team straight away rather than saved for your next appointment.
What did the DESTINY-Breast04 trial show?
In the DESTINY-Breast04 trial, people with HER2-low secondary breast cancer lived longer, and went longer before their cancer grew or spread, on Enhertu than on chemotherapy4.
The trial included 557 people with HER2-low secondary breast cancer who had already had one or two chemotherapy treatments for secondary disease, or whose cancer had come back within 6 months of adjuvant chemotherapy. Of these, 494 had HR+ breast cancer and 63 had hormone receptor-negative breast cancer (triple negative). People were randomly assigned to have either Enhertu or a chemotherapy chosen by their doctor4.
The results are given as medians. A median is the midpoint: half of the people in the group did better than this figure, and half did not do as well.
How long did people go before the cancer grew or spread?
Overall, the median time before the cancer grew or spread (progression-free survival) was 9.9 months on Enhertu compared with 5.1 months on chemotherapy, a difference of 4.8 months. Enhertu halved the risk of the cancer growing or spreading during the trial. In the HR+ group, the figures were 10.1 months compared with 5.4 months, and in the triple negative group, 8.5 months compared with 2.9 months4 (figure 3).
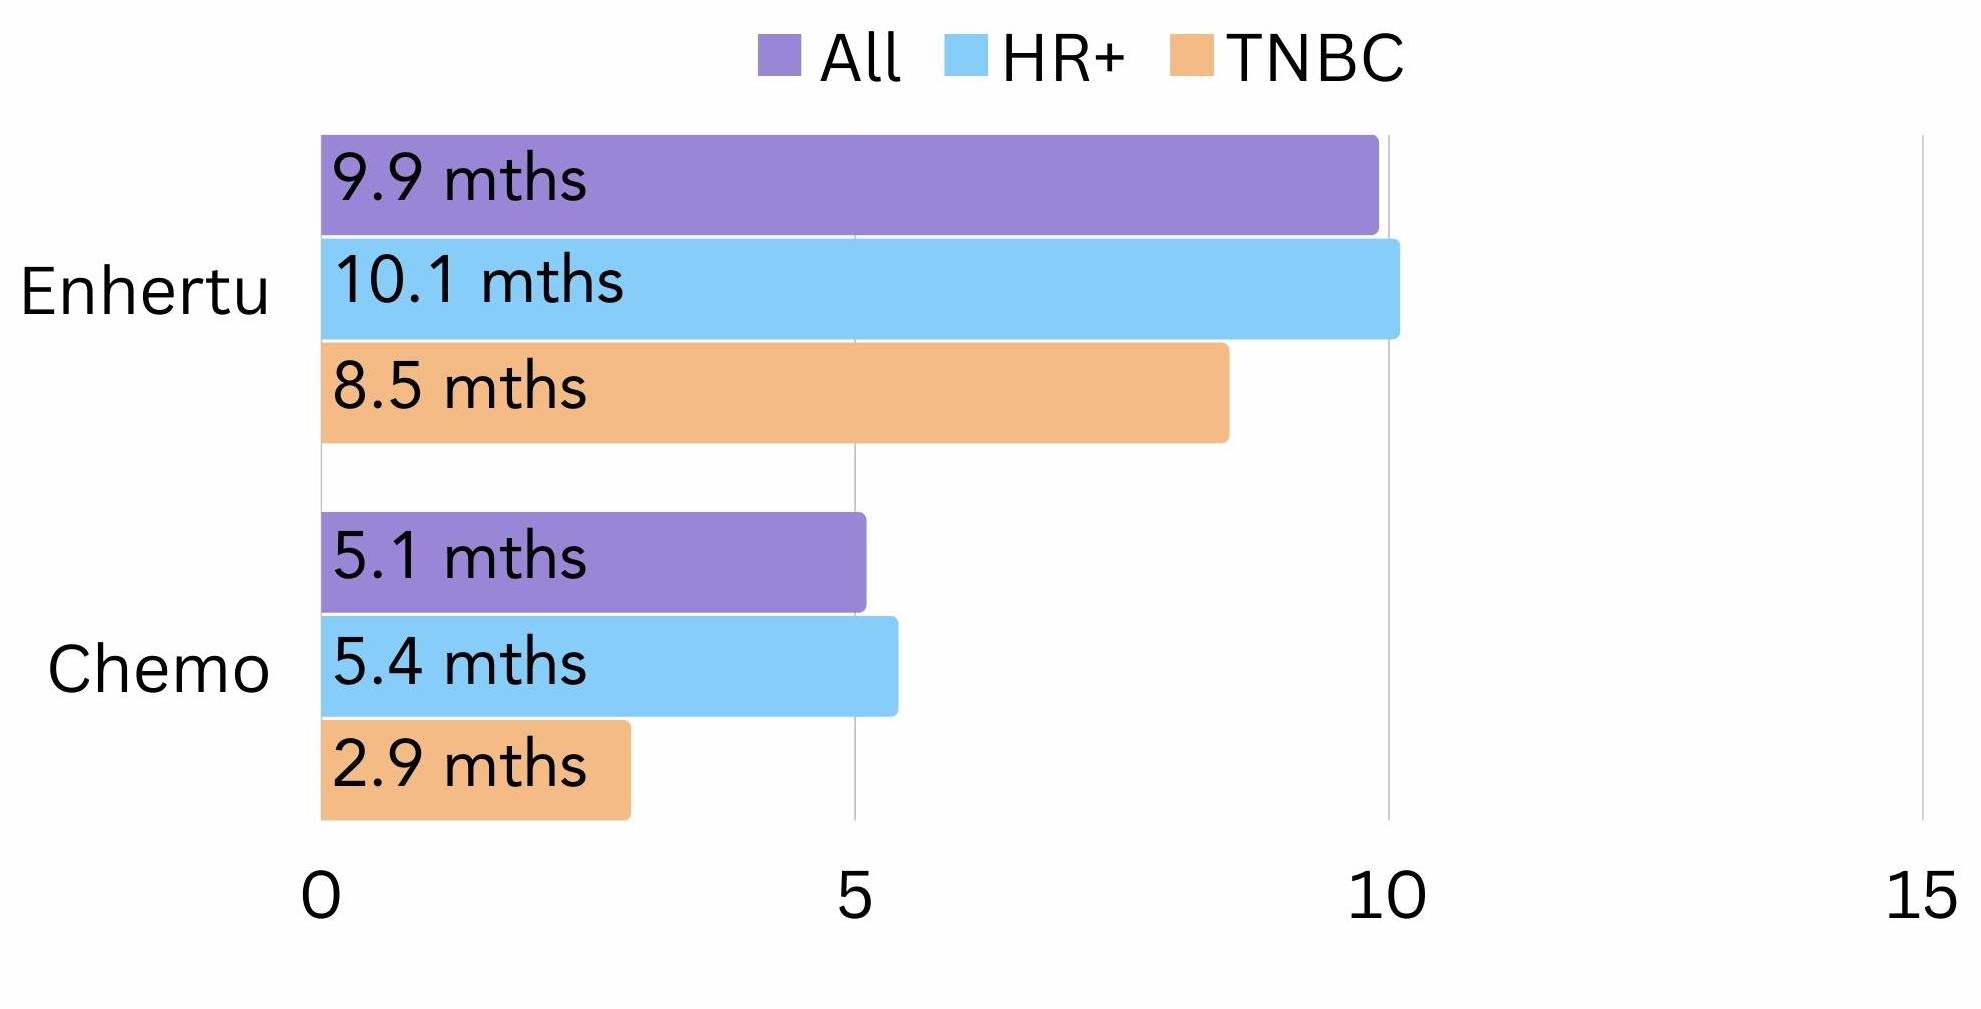
Figure 3. Median time before the cancer grew or spread (progression-free survival) on trastuzumab deruxtecan (Enhertu®) compared with chemotherapy in the DESTINY-Breast04 trial, for all patients, the HR+ group and the triple negative (TNBC) group.
How long did people live?
Overall, median survival was 23.4 months on Enhertu compared with 16.8 months on chemotherapy, a difference of 6.6 months, and Enhertu reduced the risk of death during the trial by around a third. In the HR+ group, median survival was 23.9 months compared with 17.5 months. In the triple negative group, it was 18.2 months compared with 8.3 months, although this group was small (63 people), so these figures are less certain4 (figure 4).
A longer follow-up analysis, published in 2025 after a median of 32 months, confirmed that the survival benefit was maintained (median 22.9 months on Enhertu compared with 16.8 months on chemotherapy overall)18.
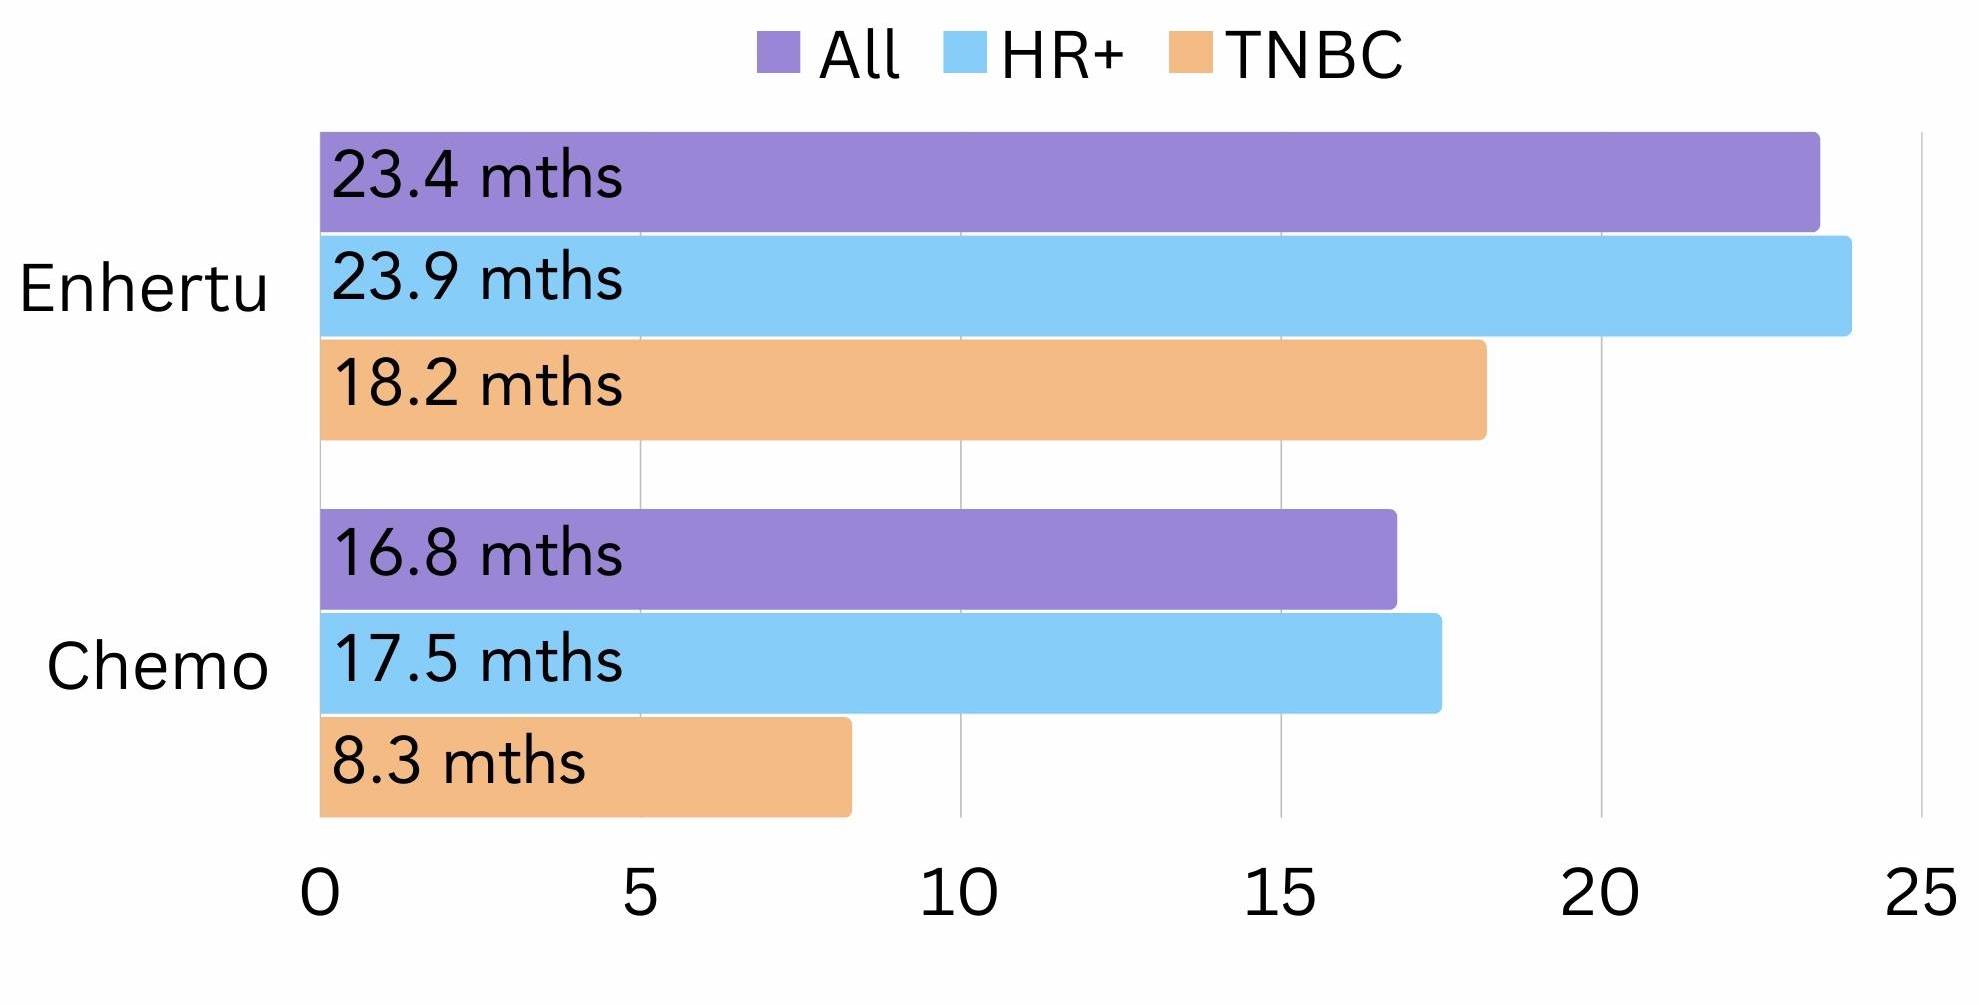
Figure 4. Median survival (overall survival) on trastuzumab deruxtecan (Enhertu®) compared with chemotherapy in the DESTINY-Breast04 trial, for all patients, the HR+ group and the triple negative (TNBC) group.
Table 3. DESTINY-Breast04 results at a glance4
| Group | Median time before cancer grew or spread | Median survival |
|---|---|---|
| All patients (557) | 9.9 months on Enhertu vs 5.1 months on chemotherapy | 23.4 months on Enhertu vs 16.8 months on chemotherapy |
| HR+ (494) | 10.1 months vs 5.4 months | 23.9 months vs 17.5 months |
| Triple negative (63) | 8.5 months vs 2.9 months | 18.2 months vs 8.3 months |
Have other HER2-targeted treatments been tested in HER2-low breast cancer?
Yes, but other HER2-targeted antibodies have not shown enough benefit to be used for HER2-low breast cancer. Trastuzumab (Herceptin®), pertuzumab (Perjeta®) and margetuximab (Margenza®) have each been tested in people with HER2-low breast cancer:
- Trastuzumab added to chemotherapy did not increase the length of time people stayed free of cancer or improve survival19.
- Pertuzumab on its own led to few responses. Combined with chemotherapy it offered a slight benefit but was linked to more side effects20,21.
- Margetuximab was not very effective and many people stopped treatment because of lack of benefit or side effects, so the trial was not completed22.
HER2-low breast cancer summed up
HER2-low is not a separate type of breast cancer. It describes breast cancers, most of them HR+, that have a small amount of HER2 on their surface (an IHC score of 1+, or 2+ with a negative ISH test). For people with secondary breast cancer, that small amount of HER2 can make trastuzumab deruxtecan (Enhertu®) a treatment option, and following the NICE recommendation it is now available for routine NHS use in England after chemotherapy. Knowing your exact IHC score, and not just whether your cancer is “HER2-negative”, can directly affect the treatment options available to you.
You may also find these blogs helpful
- Secondary (Metastatic) HR+ Breast Cancer: Your Treatment Options
- Secondary Triple Negative Breast Cancer (TNBC)
- HER2 Secondary Breast Cancer: All of the Treatments Explained
- Secondary Breast Cancer: Pathology, Signs and Diagnosis
- Understanding Your Pathology Report.
Questions to ask your care team
- What is my HER2 IHC score, and does that mean my cancer is HER2-low, HER2-ultralow or HER2-zero?
- Was my HER2 status tested on my secondary cancer, or only on my original tumour? Would a retest be helpful?
- Could Enhertu be an option for me now, or later in my treatment?
- What side effects should I look out for on Enhertu, and who should I call if I get a cough or feel short of breath?
- How will my lungs be monitored while I am having Enhertu?
- Are there any clinical trials for HER2-low or HER2-ultralow breast cancer that I could take part in?
A “HER2-negative” label should not be the reason a treatment option is missed. Keep your pathology results, your HER2 score and your questions together in the free OWise app, so you can ask at your next appointment whether a HER2-low treatment could be right for you, and track how you feel day by day if you start it.
Editorial information
Written by: OWise editorial team | Clinically reviewed by: A. Bruinvels, MSc PhD | Last reviewed: September 2026
References
- Tarantino P, Hamilton E, Tolaney SM, et al. HER2-Low Breast Cancer: Pathological and Clinical Landscape. Journal of Clinical Oncology. 2020;38(17):1951-1962.
- Bardia A, Hu X, Dent R, et al. Trastuzumab Deruxtecan after Endocrine Therapy in Metastatic Breast Cancer. New England Journal of Medicine. 2024;391(22):2110-2122. https://www.nejm.org/doi/abs/10.1056/NEJMoa2407086
- Atallah NM, Haque M, Quinn C, et al. Characterisation of luminal and triple-negative breast cancer with HER2 Low protein expression. European Journal of Cancer. 2023;195:113371. https://doi.org/10.1016/j.ejca.2023.113371
- Modi S, Jacot W, Yamashita T, et al. Trastuzumab Deruxtecan in Previously Treated HER2-Low Advanced Breast Cancer. New England Journal of Medicine. 2022;387(1):9-20. https://www.nejm.org/doi/full/10.1056/NEJMoa2203690
- Cancer Network. Future Outlook for Treatment of HER2-Low and Triple-Negative Breast Cancers. Cancer Network. 2023 Mar 21 [accessed 2023 Aug 9].
- FDA. FDA Approves First Targeted Therapy for HER2-Low Breast Cancer. FDA. 2022 Aug 5. https://www.fda.gov/news-events/press-announcements/fda-approves-first-targeted-therapy-her2-low-breast-cancer
- EMA. Enhertu: EPAR. European Medicines Agency. https://www.ema.europa.eu/en/medicines/human/EPAR/enhertu
- NICE. NICE recommends Enhertu for people with HER2-low advanced breast cancer. NICE. 2026 Sep 17. https://www.nice.org.uk/news/articles/nice-recommends-enhertu-for-people-with-her2-low-advanced-breast-cancer
- The Pharmaceutical Journal. Breast cancer drug Enhertu recommended for NHS use. The Pharmaceutical Journal. 2026. doi:10.1211/PJ.2026.1.429648. https://pharmaceutical-journal.com/article/news/breast-cancer-drug-enhertu-recommended-for-nhs-use
- FDA. FDA approves fam-trastuzumab deruxtecan-nxki for unresectable or metastatic HR-positive, HER2-low or HER2-ultralow breast cancer. FDA. 2025 Jan 27.
- AstraZeneca. Enhertu approved in the EU as first HER2-directed therapy for patients with HR-positive, HER2-low or HER2-ultralow metastatic breast cancer following at least one endocrine therapy. AstraZeneca. 2025 Apr 4. https://www.astrazeneca.com/media-centre/press-releases/2025/enhertu-approved-in-eu-in-post-et-breast-cancer.html
- Kostova V, Désos P, Starck J-B, Kotschy A. The Chemistry Behind ADCs. Pharmaceuticals. 2021;14(5):442.
- American Cancer Society. Monoclonal Antibodies and Their Side Effects. American Cancer Society. 2022. https://www.cancer.org/cancer/managing-cancer/treatment-types/immunotherapy/monoclonal-antibodies.html
- American Cancer Society. How Chemotherapy Drugs Work. American Cancer Society. 2019 Nov 22. https://www.cancer.org/cancer/managing-cancer/treatment-types/chemotherapy/how-chemotherapy-drugs-work.html
- Peters C, Brown S. Antibody-drug conjugates as novel anti-cancer chemotherapeutics. Bioscience Reports. 2015;35(4):e00225.
- EMA. Enhertu: Summary of Product Characteristics. European Medicines Agency. https://www.ema.europa.eu/en/documents/product-information/enhertu-epar-product-information_en.pdf
- Daiichi Sankyo, Inc. and AstraZeneca. Mechanism of Action, ENHERTU® (fam-trastuzumab deruxtecan-nxki). https://www.enhertuhcp.com/en/gastric/about-enhertu/mechanism-of-action
- Modi S, Jacot W, Iwata H, et al. Trastuzumab deruxtecan in HER2-low metastatic breast cancer: long-term survival analysis of the randomized, phase 3 DESTINY-Breast04 trial. Nature Medicine. 2025;31(12):4205-4213. https://www.nature.com/articles/s41591-025-03981-4
- Fehrenbacher L, Cecchini RS, Geyer Jr CE, et al. NSABP B-47/NRG Oncology Phase III Randomized Trial Comparing Adjuvant Chemotherapy With or Without Trastuzumab in High-Risk Invasive Breast Cancer Negative for HER2 by FISH and With IHC 1+ or 2+. Journal of Clinical Oncology. 2020;38(5):444-453.
- Gianni L, Lladó A, Bianchi G, et al. Open-Label, Phase II, Multicenter, Randomized Study of the Efficacy and Safety of Two Dose Levels of Pertuzumab, a Human Epidermal Growth Factor Receptor 2 Dimerization Inhibitor, in Patients With Human Epidermal Growth Factor Receptor 2-Negative Metastatic Breast Cancer. Journal of Clinical Oncology. 2010;28(7):1131-1137.
- Schneeweiss A, Park-Simon T-W, Albanell J, et al. Phase Ib study evaluating safety and clinical activity of the anti-HER3 antibody lumretuzumab combined with the anti-HER2 antibody pertuzumab and paclitaxel in HER3-positive, HER2-low metastatic breast cancer. Investigational New Drugs. 2018;36(5):848-859.
- ClinicalTrials.gov. Phase 2 Study of the Monoclonal Antibody MGAH22 (Margetuximab) in Patients With Relapsed or Refractory Advanced Breast Cancer: Study Results. 2022 [accessed 2023 Aug 9]. https://classic.clinicaltrials.gov/ct2/show/results/NCT01828021