
Hormone receptor-positive (HR+), HER2-negative early breast cancer

If you have been diagnosed with hormone receptor-positive (HR+), HER2-negative early breast cancer, you have the most common type of breast cancer, and there are several effective ways to treat it. This guide explains what HR+ means, how your receptor results are reported, and how your care team decides between hormone therapy, the CDK4/6 inhibitors abemaciclib and ribociclib, olaparib and chemotherapy. It is written for anyone newly diagnosed or already on treatment who wants to understand their options and feel ready for their next appointment.
Key takeaways
- Around 3 in 4 breast cancers are hormone receptor-positive, meaning oestrogen and/or progesterone help the cancer grow. A test result of 1% or more counts as positive.
- Hormone therapy is the main treatment. Tamoxifen is usually used before the menopause and aromatase inhibitors after it, for at least 5 years and sometimes up to 10.
- If your risk of the cancer coming back is high, adding a CDK4/6 inhibitor (abemaciclib for 2 years or ribociclib for 3 years) to hormone therapy lowers that risk. Both are recommended by NICE.
- If you have an inherited BRCA1 or BRCA2 gene change and high-risk cancer, olaparib for 1 year after chemotherapy is another NICE-recommended option.
- Genomic tests such as Oncotype DX, EndoPredict and Prosigna can help show whether chemotherapy is likely to benefit you.
- Hormone therapy can last 5 to 10 years. The OWise app lets you track side effects such as joint pain or hot flushes over time, so you and your care team can deal with them before they make you want to stop treatment.
In this article
- What is hormone receptor-positive (HR+) breast cancer?
- How common is hormone receptor-positive breast cancer?
- How do I know if my breast cancer is HR+?
- How do oestrogen and progesterone cause cancer growth?
- What treatments are used for early HR+ breast cancer?
- What is hormone (endocrine) therapy?
- How does my risk of recurrence affect my treatment?
- Which targeted treatments are used for high-risk early HR+ breast cancer?
- Can I avoid chemotherapy?
- When is chemotherapy recommended?
- Side effects of hormone therapy, targeted treatments and chemotherapy
- Questions to ask your care team
Around 75% 1,2,3 of breast cancers are thought to be influenced by oestrogen and progesterone. They are both hormones that travel in the blood to tell other parts of the body how to function. In women, oestrogen and progesterone are the vital sex hormones that regulate menstrual cycles and play an important role in pregnancy.
In HR+ breast cancer these hormones have a very different function. When they attach to receptors on the cancer cells, they stimulate them to grow. This discovery has led to a whole new category of treatment called hormone therapy.
This article focuses on hormone receptor-positive, HER2-negative breast cancer. If your cancer is HER2-positive, read our guide to HER2-positive breast cancer.
How common is hormone receptor-positive breast cancer?
Hormone receptor-positive (HR+) breast cancer that is negative for the protein HER2 (see our HER2 blog) is the most common subtype of breast cancer. Around 7 in 10 breast cancers are HR+ and HER2-negative. Longer or greater exposure to oestrogen over a lifetime is thought to increase the risk of HR+ breast cancer, for example through starting periods at a younger age, a higher body mass index and use of hormone replacement therapy (HRT) after the menopause4.
Did you know? Breast cancer was once referred to as “Nun’s Disease”. A study conducted in 1969 compiled cancer mortality rates in 32,000 Catholic nuns in the USA between 1900 and 1954. They found that nuns had an increased probability of dying from breast, ovarian, and uterine cancer compared with the female population5. This link is thought to be explained by the number of ovulatory menstrual cycles a woman has. Epidemiological studies have found an increased number of cycles increases risk due to the increased exposure to oestrogen. Hence, giving birth, breastfeeding and age of puberty and menopause all influence risk of breast cancer.
It’s important to point out that HR+ breast cancer affects men too. While men have higher levels of male sex hormones (androgens), they also have low levels of circulating oestrogen. 80% of circulating oestrogen is produced through the aromatase pathway (you’ll find out more about that later) and 20% directly by the testes. Around 9 in 10 breast cancers in men are HR+, and the hormone therapy we will discuss throughout this blog is also given to men6. Tamoxifen is the usual hormone therapy for men. If an aromatase inhibitor is used, it is given with an injection that lowers testosterone (an LHRH agonist), because on its own it does not lower oestrogen enough in men28.
How do I know if my breast cancer is HR+?
Your cancer is tested for hormone receptors in the laboratory, usually on tissue from your biopsy and again on the tissue removed during surgery. The same sample is also tested for HER2. Results for oestrogen receptors (ER) and progesterone receptors (PR) are given either as a score from 0 to 8 (called an Allred or Quick score) or as the percentage of cancer cells that have the receptor. The higher the score, the more receptors the cancer cells have. A score of 3 or more, or a result of 1% or more, means the cancer is hormone receptor-positive7.
If only 1% to 10% of the cancer cells have oestrogen receptors, your report may describe the cancer as ER-low positive. These cancers can behave more like hormone receptor-negative breast cancer, so hormone therapy may be less helpful and your team may talk to you about other treatments as well7. Read our guide to your pathology report to understand each of your results.
Not sure what the ER, PR and HER2 results on your pathology report mean for your treatment? Answer a few questions about your diagnosis in the OWise app to get personalised information about your type of breast cancer and your treatment options, plus tailored questions to take to your next appointment.
How do oestrogen and progesterone cause cancer growth?
Oestrogen and progesterone bind to receptors in cancer cells that are directly involved in switching genes on and off, changing the cell’s behaviour. When oestrogen binds to its receptor, it turns on genes that tell the cells to keep dividing, driving tumour growth.
The function of progesterone is still under debate. However, research published in 2015 suggests that progesterone may actually help to slow down cancer growth8. Once progesterone bound to its receptor, different genes were turned on and off, causing a decrease in the growth of cells. What this means for the future of hormonal treatment is not yet known. 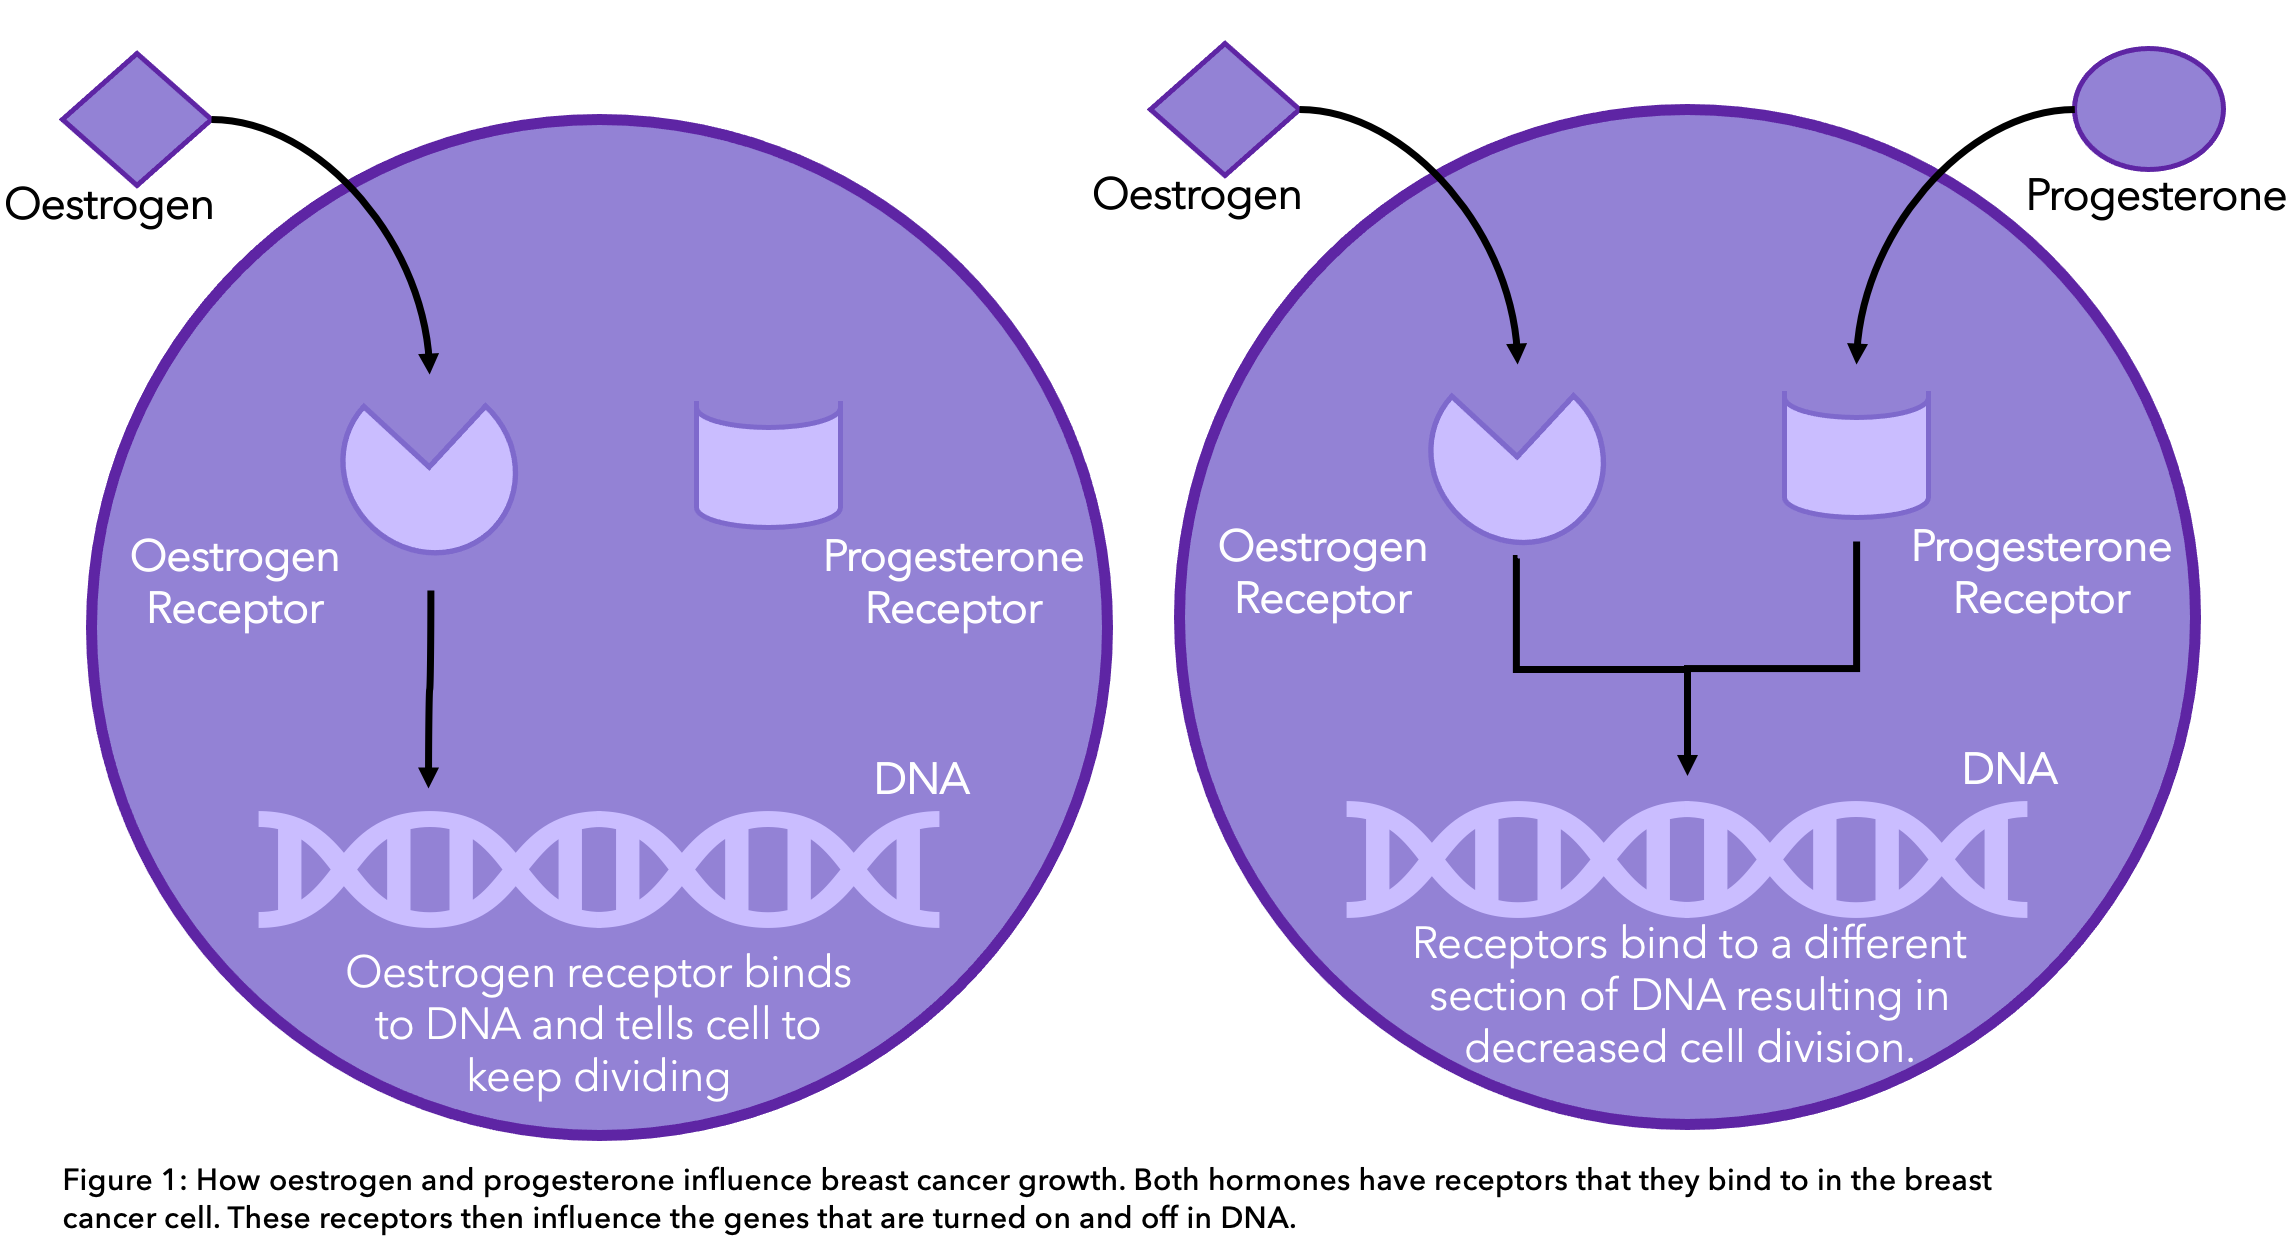
What treatments are used for early HR+ breast cancer?
Most people with early HR+ breast cancer have surgery, often followed by radiotherapy, and then take hormone therapy for at least 5 years. Depending on the risk of the cancer coming back, your team may also recommend chemotherapy, a targeted drug (a CDK4/6 inhibitor or olaparib) or a bisphosphonate. The table below summarises the main medicines recommended by NICE for use on the NHS, and each is explained in more detail further down. In Scotland, medicines are assessed separately by the Scottish Medicines Consortium.
Early HR+ breast cancer treatments at a glance
| Treatment | Who it is usually for | How long |
|---|---|---|
| Tamoxifen | Most people before the menopause, and men. Some people after the menopause with a low risk of recurrence | 5 years, sometimes up to 10 |
| Aromatase inhibitor (anastrozole, letrozole, exemestane) | People after the menopause. Before the menopause, only together with ovarian suppression | 5 years, sometimes up to 10 in total |
| Ovarian suppression (for example goserelin) | People before the menopause with a higher risk of recurrence | Often up to 5 years |
| Abemaciclib (Verzenios) with hormone therapy | Cancer in the lymph nodes at high risk: 4 or more affected nodes, or 1 to 3 nodes with grade 3 cancer or a tumour of 5 cm or more | 2 years |
| Ribociclib (Kisqali) with an aromatase inhibitor | Stage II or III at high risk, including any lymph node involvement and some node-negative cancers with high-risk features | 3 years |
| Olaparib (Lynparza) | Inherited BRCA1 or BRCA2 change with high-risk HER2-negative cancer, after chemotherapy | 1 year |
| Bisphosphonates (zoledronic acid or sodium clodronate) | After the menopause with cancer in the lymph nodes; considered for high-risk node-negative cancer | Usually 2 to 3 years |
| Chemotherapy | Higher risk of recurrence, or when a genomic test suggests benefit | Usually 3 to 6 months |
What is hormone (endocrine) therapy?
Hormone therapy blocks hormones and hormone receptors, suppressing their influence in promoting breast cancer growth. The treatment options available for women depend on whether they are pre- or post-menopausal. This is because oestrogen is produced in different places and therefore treatments need to target different areas.
For premenopausal women, the main source of oestrogen and progesterone is the ovaries. In postmenopausal women, once the menstrual cycle has ceased, the main source of oestrogen is from the aromatase pathway. This is where androgens created in the adrenal glands and ovaries are converted to oestrogen. This happens all over the body, including in the liver, muscle but most significantly in the fat under the skin.
What hormone therapy is used before the menopause?
For premenopausal women and male patients, tamoxifen in the form of an oral tablet is the most commonly prescribed hormone therapy. It works by blocking the oestrogen receptors on the cancer cells. This way, oestrogen is still present in normal amounts in the body, but it cannot activate the cancer cells to grow further (see diagram). 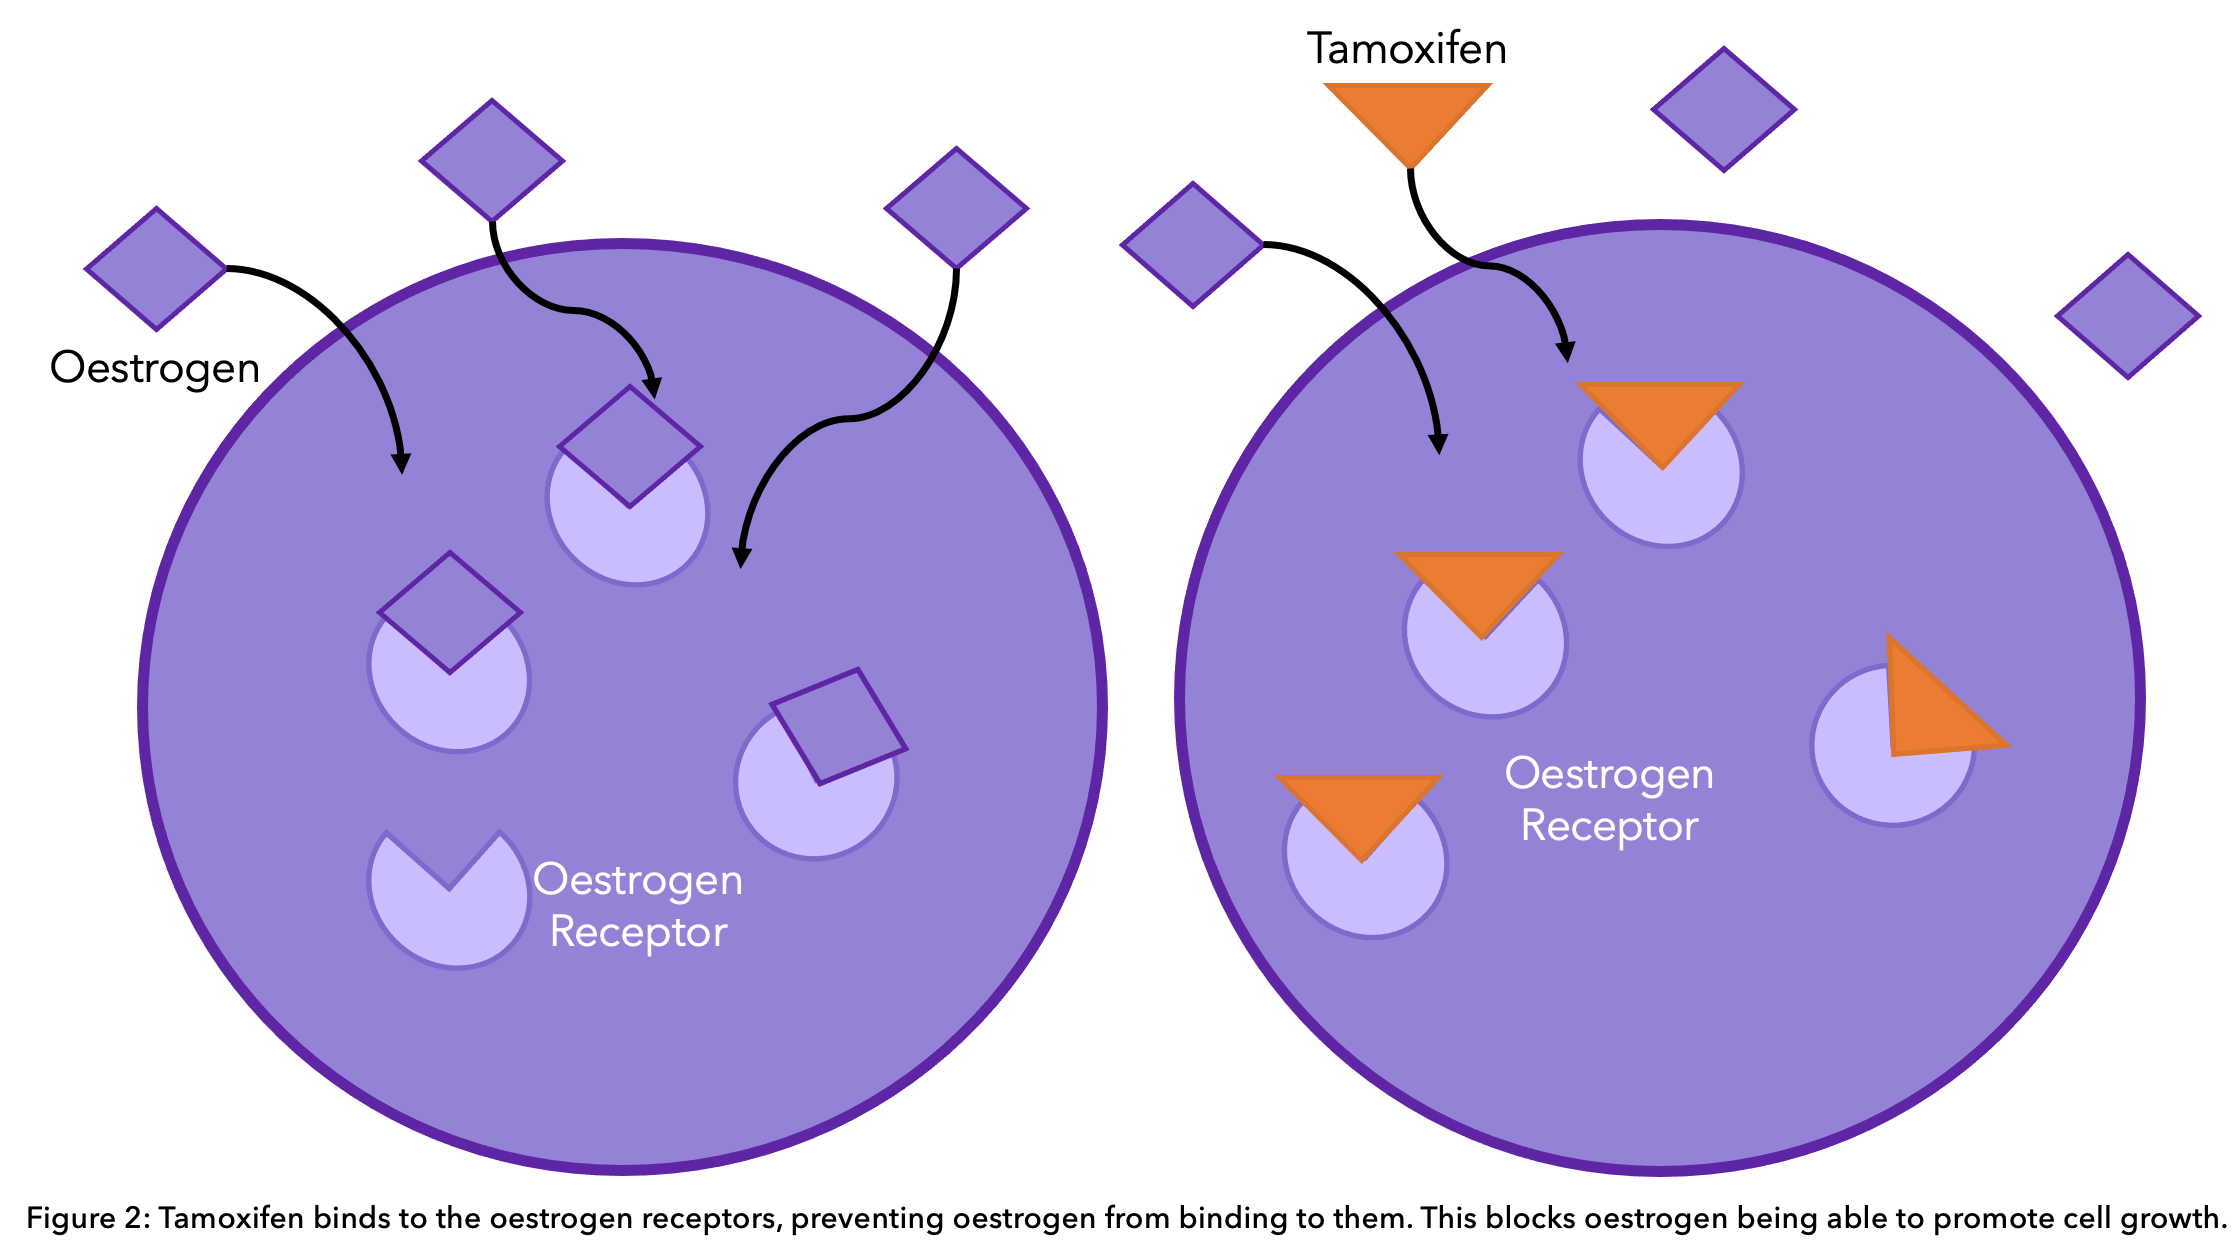
Did you know? Tamoxifen was originally created as a contraceptive pill. Scientists in the 1960s synthesised the drug hoping it would block oestrogen and act as an effective contraceptive. However, during testing, they found that tamoxifen stimulated, rather than suppressed, ovulation in women9.
Premenopausal women can also be offered treatment that suppresses the function of their ovaries. This therapy is termed ovarian suppression or ovarian ablation. It will be either offered through the removal of the ovaries or treatment that prevents the ovaries from functioning for a limited period of time. Ovarian suppressors block the brain from telling the ovaries how to work. This stops the ovaries from functioning and therefore decreases the presence of oestrogen and progesterone in the body10. The most common ovarian suppressors are11:
- Goserelin (Zoladex®)
- Buserelin (Suprefact®)
- Triptorelin (Decapeptyl®)
- Leuprorelin (Prostap®)
Ovarian suppressors are given as injections, usually every 4 weeks or every 3 months depending on the drug. They are given alongside tamoxifen or an aromatase inhibitor. The inclusion of ovarian suppressors should be discussed with your doctor and more likely will be offered if there is a high risk of cancer recurrence12. High risk may include people who have lymph-node positive disease (stage N1 or above), tumours that are T2 (2-5 cm across) or greater, and a higher grade, meaning they look significantly different from normal breast cells.
Aromatase inhibitors do not work on their own before the menopause, because the ovaries keep making oestrogen. Given together with ovarian suppression, however, an aromatase inhibitor can lower the risk of recurrence more than tamoxifen with ovarian suppression in premenopausal women at higher risk29. Ovarian suppression brings on menopausal symptoms, so talk to your team about the likely side effects, and about fertility if you may want children in the future, before you start.
What hormone therapy is used after the menopause?
Aromatase inhibitors are the most common hormone therapy offered to postmenopausal women. They work by preventing the enzyme “aromatase” from converting other hormones into oestrogen, thus lowering the amount of oestrogen in the body13. These are particularly effective in postmenopausal women due to the aromatase pathway being primarily responsible for oestrogen production. 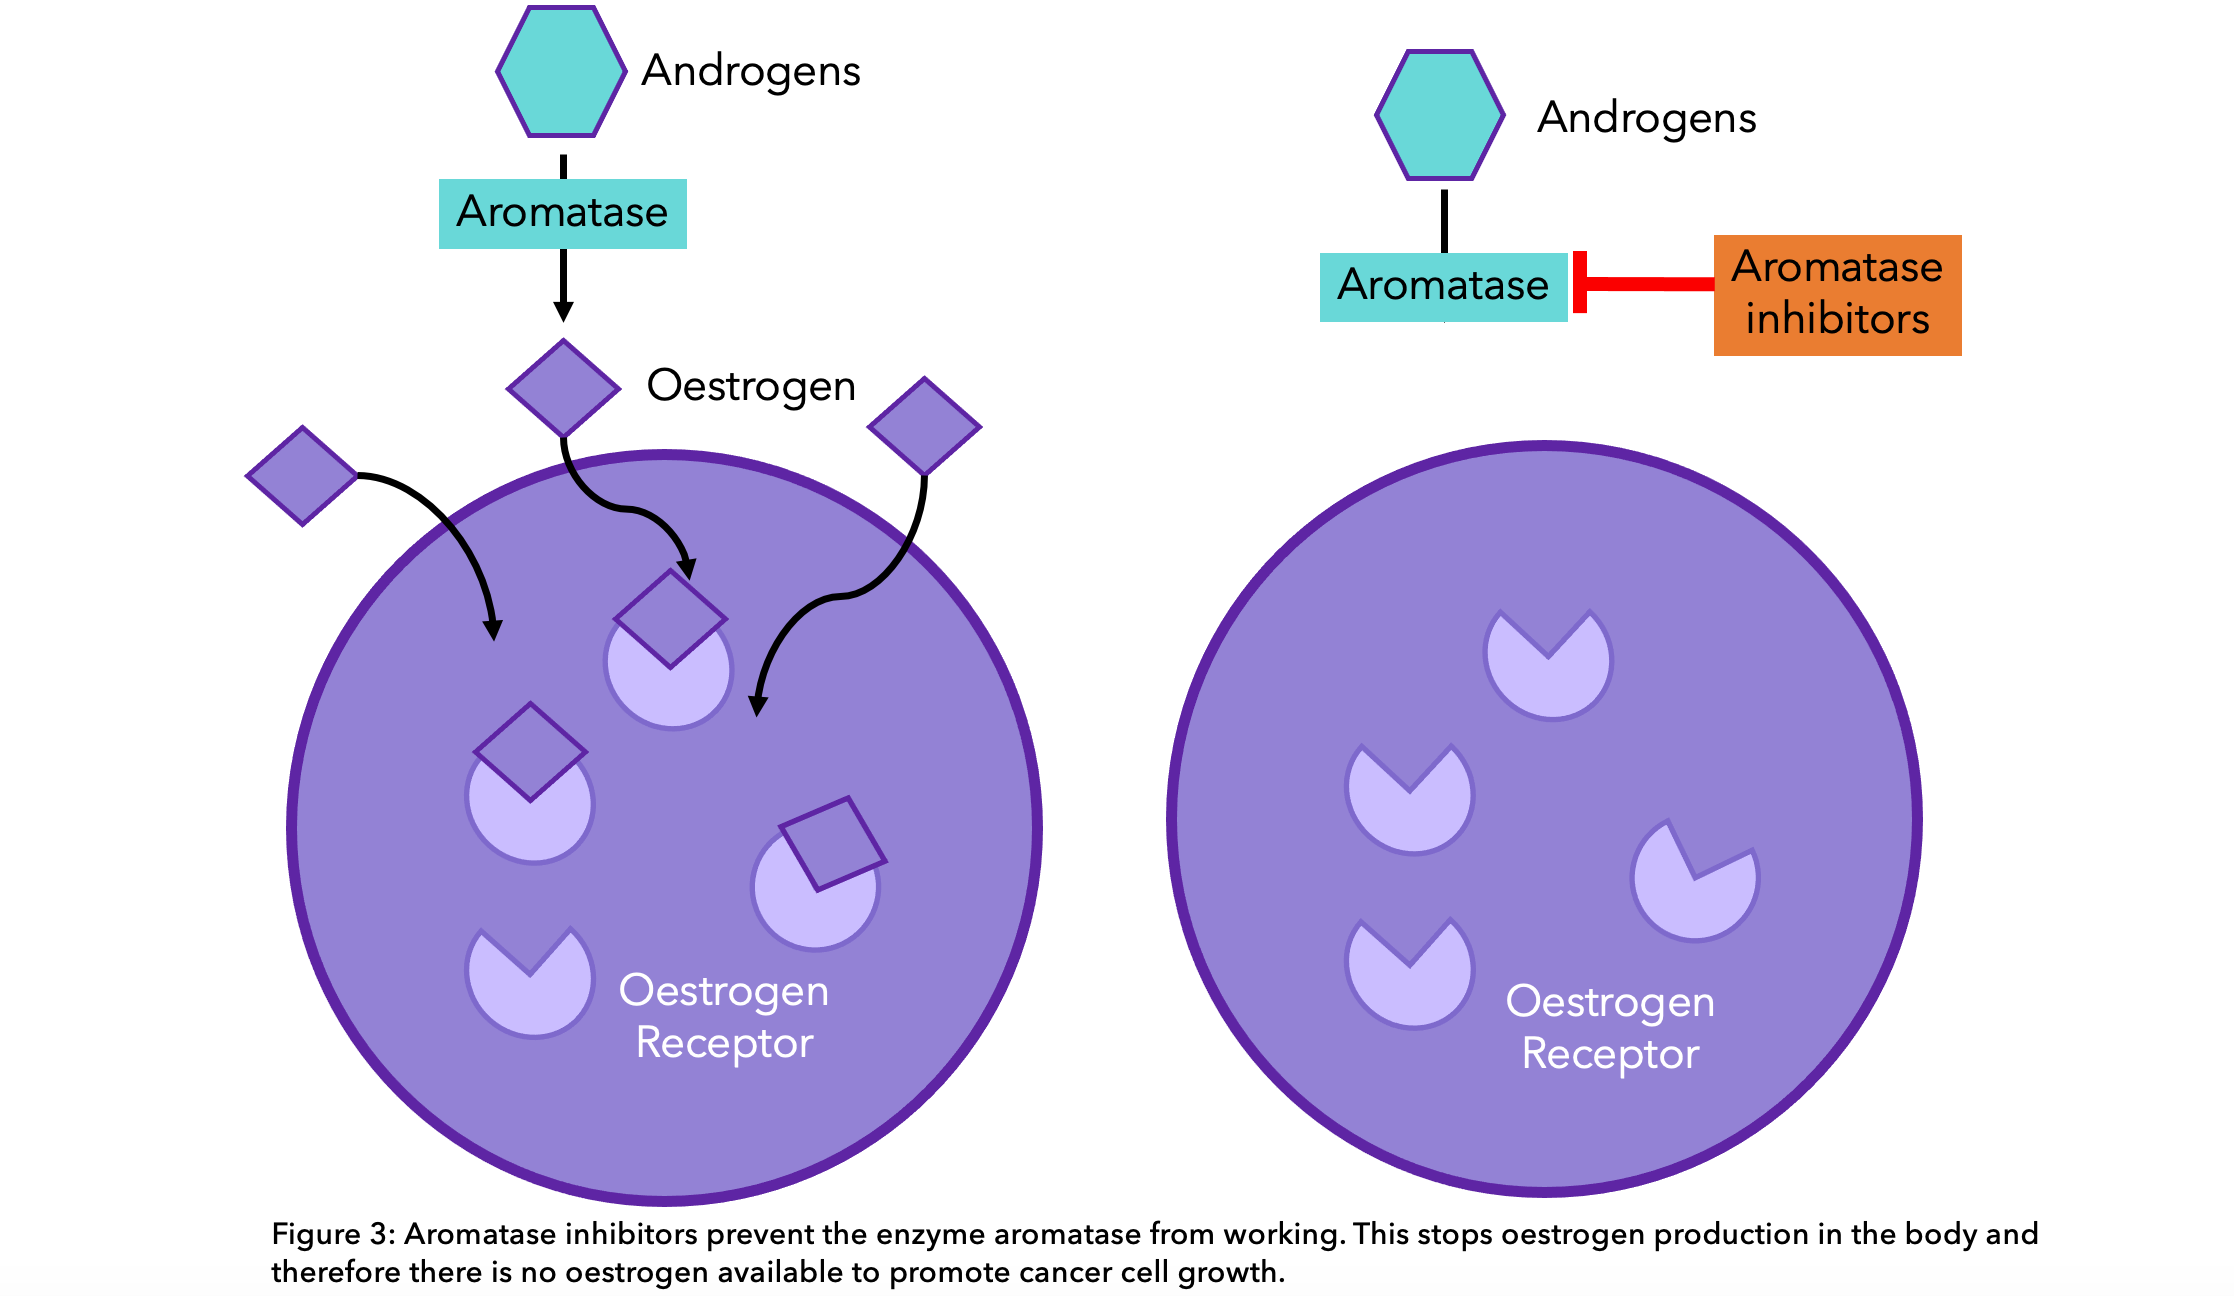 The aromatase inhibitors available in the NHS are13:
- Letrozole (Femara®)
- Anastrozole (Arimidex®)
- Exemestane (Aromasin®)
These have been found to decrease circulating oestrogen to very low levels14, thereby reducing tumour growth15. The three medicines work similarly well, and the choice of which to have will be between you and your doctor. Postmenopausal women are at increased risk of a decrease in bone density (osteoporosis) due to a lack of circulating oestrogens in their body, which can then be accentuated through aromatase inhibitor treatment. You should have a bone density (DEXA) scan when you start an aromatase inhibitor. NICE also recommends offering bisphosphonates (zoledronic acid or sodium clodronate) to postmenopausal women whose breast cancer has spread to the lymph nodes, and considering them for those at high risk whose lymph nodes are clear. Given this way (adjuvant bisphosphonates), they lower the risk of breast cancer coming back in the bones and help protect bone density12.
Could I have hormone therapy before surgery?
For some people, yes. Hormone therapy given before surgery (neoadjuvant hormone therapy) can shrink the tumour, which may make surgery easier or make breast-conserving surgery possible instead of a mastectomy. NICE suggests considering it for postmenopausal women with ER-positive breast cancer when there is no clear reason to have chemotherapy. It usually needs to be taken for several months before surgery. Whether hormone therapy or chemotherapy is the better option before surgery depends on your menopausal status and the features of your cancer, and is something to decide with your care team12.
How does my risk of recurrence affect my treatment?
The risk of cancer coming back can be evaluated through looking at various factors. This includes whether the cancer has spread to your lymph nodes, how large the tumour is, and how different the tumour cells look compared to normal breast cells. The outcome of this evaluation will affect the treatment you will be given. Genomic profiling tests (see below) and the PREDICT tool can also help you and your team decide on the best treatment for your cancer.
For postmenopausal women with a low risk of cancer recurrence, for example if there was no cancer in their lymph nodes, then tamoxifen may be offered instead of aromatase inhibitors. This can also be the case if aromatase inhibitors are not tolerated, which is the case for some women. Both treatments significantly reduce rates of recurrence16.
For people with cancer cells in the lymph nodes or a larger, abnormal-looking tumour, extended hormone therapy may be offered. This means continuing with tamoxifen or an aromatase inhibitor beyond 5 years, so that you take hormone therapy for up to 10 years in total. If you are postmenopausal and have been taking tamoxifen for 2-5 years, NICE recommends extending treatment with an aromatase inhibitor, as this improves the chance of staying free of cancer12. This may also be considered even if you are at low risk of recurrence.
Which targeted treatments are used for high-risk early HR+ breast cancer?
If your cancer has a higher risk of coming back, adding a targeted drug to your hormone therapy can lower that risk. Two CDK4/6 inhibitors, abemaciclib and ribociclib, are recommended by NICE for HR+, HER2-negative early breast cancer at high risk of recurrence18,19. CDK4/6 inhibitors block two proteins, cyclin-dependent kinases 4 and 6, that cancer cells need in order to divide. They are taken as tablets alongside hormone therapy and were first used for secondary (metastatic) breast cancer. For people with an inherited BRCA gene change, olaparib is another option26.
Who can have abemaciclib?
Abemaciclib (Verzenios®) with hormone therapy is recommended by NICE for people with HR+, HER2-negative early breast cancer that has spread to the lymph nodes and has a high risk of coming back. High risk means you have at least 4 affected lymph nodes, or 1 to 3 affected lymph nodes together with either grade 3 cancer or a tumour of at least 5 cm18,22. Read our guide to your pathology report for more information on tumour grade and other markers.
Abemaciclib is taken as a tablet twice a day for 2 years, alongside at least 5 years of hormone therapy. The monarchE trial included more than 5,600 men and women with high-risk early breast cancer. After 7 years, 77.4% of people who had abemaciclib with hormone therapy were alive and free of invasive cancer, compared with 70.9% of those who had hormone therapy alone. That is a difference of 6.5 percentage points, or about a 27% lower risk of invasive cancer coming back. Abemaciclib also helped people live longer: at 7 years, 86.8% were alive compared with 85.0%, a difference of 1.8 percentage points (about a 16% lower risk of death). The larger benefit is in stopping the cancer from coming back21,22.
Who can have ribociclib?
Ribociclib (Kisqali®) with an aromatase inhibitor is recommended by NICE for people with stage II or III HR+, HER2-negative early breast cancer at high risk of coming back19. This covers a wider group than abemaciclib. It includes people with any cancer in the lymph nodes (apart from tiny deposits called micrometastases), and some people whose lymph nodes are clear, for example if the tumour is larger than 5 cm, or is 2 to 5 cm and either grade 3, or grade 2 with a high Ki-67 (a measure of how fast the cells are dividing) or a high-risk genomic test result. Before the menopause, and in men, the aromatase inhibitor is combined with an injection that switches off hormone production by the ovaries or testes (an LHRH agonist)19.
Ribociclib is taken as a tablet once a day for 3 weeks, followed by a week off, for 3 years. In the NATALEE trial of 5,101 people, after 5 years 85.5% of those taking ribociclib with an aromatase inhibitor were alive and free of invasive cancer, compared with 81.0% of those taking an aromatase inhibitor alone. That is a difference of 4.5 percentage points, or about a 28% lower risk of invasive cancer coming back. Results for overall survival are still being collected24.
Abemaciclib and ribociclib have not been compared with each other in a trial. If you could have either, your team will help you weigh up the schedule and side effects of each. A third CDK4/6 inhibitor, palbociclib, is not used for early breast cancer because trials did not show a benefit. Read our guide to CDK4/6 inhibitors for more on how these medicines work.
Is olaparib an option if I have a BRCA gene change?
If you have an inherited (germline) change in the BRCA1 or BRCA2 gene and high-risk HER2-negative early breast cancer, NICE recommends olaparib (Lynparza®) tablets for 1 year after chemotherapy, on their own or with hormone therapy26. In the OlympiA trial, olaparib lowered the chance of the cancer coming back and helped people live longer26. Read our guide to BRCA gene mutations to find out who is offered genetic testing.
What new treatments are being researched?
New hormone therapies called oral SERDs (selective oestrogen receptor degraders), which block the oestrogen receptor and help break it down, are being tested in early breast cancer. In the lidERA trial, 4,170 people with medium or high risk early HR+ breast cancer took either the oral SERD giredestrant or standard hormone therapy (tamoxifen or an aromatase inhibitor). After 3 years, 92.4% of those taking giredestrant were alive and free of invasive cancer, compared with 89.6% on standard hormone therapy, a difference of 2.8 percentage points, or a 30% lower risk27. Giredestrant is investigational. It is not approved in the UK, and a decision by the US regulator (FDA) is expected by the end of November 2026. Ask your team whether there are clinical trials that could be suitable for you.
Been told you might be able to have abemaciclib, ribociclib or olaparib? Decisions like this are often made in a single appointment, and it can be hard to take everything in. Use the OWise app to note your questions beforehand, such as whether you meet the criteria and which side effects to look out for, and record the conversation so you can listen back at home.
Can I avoid chemotherapy?
Not everyone with early HR+ breast cancer needs chemotherapy, and genomic tests help show who is likely to benefit. They measure the activity of a group of genes in a sample of your tumour and give a score for how likely the cancer is to come back, which also helps show how much chemotherapy would add to hormone therapy. The tests used in the NHS are Oncotype DX®17, EndoPredict® and Prosigna®20. NICE recommends them for people with HR+, HER2-negative early breast cancer when:
- your lymph nodes are clear, or contain only tiny deposits of cancer (micrometastases), and your risk of recurrence is intermediate on a tool such as PREDICT, or
- you have 1 to 3 affected lymph nodes and have been through the menopause (the tests can also be used for men).
For women with 1 to 3 affected lymph nodes who have not been through the menopause, NICE does not recommend using these tests to decide on chemotherapy, as evidence suggests chemotherapy may still help this group whatever their score20. Your specialist will use your score, along with other information about your cancer, to help you decide together whether chemotherapy is worthwhile. These tumour tests are different from genetic tests for inherited gene changes such as BRCA, which look at your own DNA rather than the cancer’s.
When is chemotherapy recommended?
Chemotherapy is a treatment that uses anti-cancer drugs to target and kill fast-dividing cells in your body. It works by interfering with the cancer cells’ ability to divide and grow. Chemotherapy may be recommended before or after surgery if your cancer has a higher risk of coming back12. The risk will depend on the grade and size of your tumour, the number of affected lymph nodes in your armpit, your age and the score you’ve received in the profiling tests we have mentioned above. In general, the larger the size of the tumour, the higher the grade, number of nodes with cancer and score, the more likely you would benefit from chemotherapy. Your team may use the PREDICT tool to show how much chemotherapy is likely to add in your situation, and you can look at the results together. Chemotherapy for early breast cancer usually includes a taxane, and often an anthracycline and cyclophosphamide. Drugs you may be offered include:
- Taxane chemotherapy drugs include paclitaxel (Taxol®) and docetaxel (Taxotere®).
- Anthracycline chemotherapy drugs include epirubicin and doxorubicin (Adriamycin®).
- Cyclophosphamide is often given alongside, for example with epirubicin (EC) or with docetaxel (TC).
What are the side effects of hormone therapy?
Common side effects of tamoxifen include hot flushes and night sweats, vaginal discharge or dryness, changes to your periods, nausea, tiredness, mood changes, headaches, leg cramps and hair thinning23. Less commonly, tamoxifen can cause blood clots and, after the menopause, changes to the lining of the womb. Tell your team straight away if you have pain or swelling in your leg, breathlessness or chest pain, or any unexpected vaginal bleeding23. Side effects of aromatase inhibitors (AIs) includesymptoms of menopause (hot flushes, vaginal dryness and night sweats) and muscle and joint pain. AIs can also lead to osteoporosis (bone thinning) and they may raise cholesterol levels13.
Our guide to tamoxifen and aromatase inhibitors has practical tips on managing these side effects.
What are the side effects of CDK4/6 inhibitors and olaparib?
The most common side effect of abemaciclib is diarrhoea, which often starts in the first few weeks. It can usually be controlled with anti-diarrhoea medicine, and your dose can be reduced if needed. Abemaciclib and ribociclib can both lower your white blood cell count (neutropenia), which can increase the risk of infection, and both can cause tiredness. Ribociclib can also affect the liver and the heart’s rhythm, so you will have regular blood tests and heart tracings (ECGs), especially in the first months of treatment21,24. Olaparib most often causes nausea, tiredness and anaemia (a low red blood cell count)26.
What are the side effects of chemotherapy?
Regarding chemotherapy, the side effects can be very diverse as chemotherapy drugs target all fast-dividing cells in your body, and the body has other fast-dividing cells apart from cancer cells such as cells at the hair follicles, the lining of the mouth, skin, nails and intestines. That’s why hair loss, brittle nails and diarrhoea are very common side-effects. Other very common side effects are sickness and vomiting. The chemotherapy drugs anthracyclines can also cause heart function problems. This is why you might have heart tests to check the health of your heart before and during chemotherapy25.
Is a side effect getting worse, or could it be linked to your latest treatment? Track more than 30 side effects and symptoms in the OWise app, from diarrhoea on abemaciclib to joint pain on an aromatase inhibitor, and share a clear picture with your care team. Spotting a pattern early gives your team the chance to adjust your dose, add supportive medicines or switch treatment, rather than you stopping a treatment that lowers your risk of the cancer coming back.
Related OWise blogs
- Understanding your breast cancer diagnosis
- Your pathology report explained
- Tamoxifen and aromatase inhibitors
- CDK4/6 inhibitors explained
- BRCA gene mutations
- Hormone therapy resistance
Questions to ask your care team
Use the OWise app to create your own question lists and add the questions below to make sure you cover everything you need:
- Is my cancer ER-positive, PR-positive or both, and is it ER-low?
- What is my risk of the cancer coming back, and how does it change my treatment plan?
- Do I meet the criteria for abemaciclib or ribociclib, and if not, why not?
- Would a genomic test such as Oncotype DX help decide whether I need chemotherapy?
- Should I be offered genetic testing for BRCA1 or BRCA2, and could olaparib be an option for me?
- Which side effects should I report straight away, and who do I contact if they happen?
Hormone therapy works best when you take it for the full course, which for early HR+ breast cancer can mean 5 to 10 years, sometimes alongside a CDK4/6 inhibitor. Side effects should not be the reason you stop a treatment that lowers your risk of the cancer coming back. Download the free OWise app to track how you feel day to day, record your appointments and keep your questions in one place, so you and your care team can find the right way forward together.
Editorial Information
Written by: OWise editorial team | Clinically reviewed by: A. Bruinvels, MSc PhD | Last reviewed: September 2026
References
- Nadji M, Gomez-Fernandez C, Ganjei-Azar P, Morales AR. 2005. Immunohistochemistry of estrogen and progesterone receptors reconsidered: experience with 5,993 breast cancers. Am J Clin Pathol. 123:21-27.
- Lange CA, Yee D. 2008. Progesterone and breast cancer. Womens Health (Lond) 4:151-162.
- Moelans CB, de Ligt J, van der Groep P, Prins P, Besselink N, Hoogstraat M, ter Hoeve N, Lacle M, Kornegoor R, van der Pol C, de Leng W, Barbe E, van der Vegt B, Martens J, Bult P, Smits VT, Koudijs M, Nijman I, Voest E, Selenica P, Weigelt B, Reis-Filho J, van der Wall E, Cuppen E, van Diest PJ. 2019. The molecular genetic make-up of male breast cancer. Endocr Relat Cancer.
- Howlader, N,. et al. 2014. US Incidence Of Breast Cancer Subtypes Defined By Joint Hormone Receptor And HER2 Status. JNCI: Journal Of The National Cancer Institute. 106(5): dju055.
- Britt, K. 2012. The plight of nuns: hazards of nulliparity. The Lancet, 379: 2322-2323.
- Dent, S. F. et al. 2010. Endocrine Therapy For Male Breast Cancer: Rates Of Toxicity And Adherence. Current Oncology, 17(5): 17-21.
- Allison KH, Hammond MEH, Dowsett M, et al. 2020. Estrogen and progesterone receptor testing in breast cancer: ASCO/College of American Pathologists guideline update. Journal of Clinical Oncology. 38(12): 1346-1366.
- Mohammed, H., Russell, I., Stark, R. et al. 2015. Progesterone receptor modulates ERα action in breast cancer. Nature. 523, 313-317.
- Quirke V. 2017. Tamoxifen from Failed Contraceptive Pill to Best-Selling Breast Cancer Medicine: A Case-Study in Pharmaceutical Innovation. Frontiers in Pharmacology. 8.
- Breast Cancer Now. 2020. Goserelin-zoladex.[online] Available at: https://breastcancernow.org/information-support/facing-breast-cancer/going-through-breast-cancer-treatment/hormone-therapy/goserelin-zoladex [Accessed 12 October 2020].
- Breast Cancer Now. 2020. Ovarian suppression and breast cancer. [online]. Available at: https://breastcancernow.org/information-support/facing-breast-cancer/going-through-breast-cancer-treatment/hormone-therapy/ovarian-suppression-breast-cancer [Accessed 12 October 2020].
- National Institute for Health and Care Excellence (NICE). 2018. Early and locally advanced breast cancer: diagnosis and management (NG101). [online] Available at: https://www.nice.org.uk/guidance/ng101 [Accessed September 2026].
- Breast Cancer Now, 2019. Aromatase inhibitors (anastrozole, exemestane and letrozole). [online]. Available at: https://breastcancernow.org/information-support/facing-breast-cancer/going-through-breast-cancer-treatment/hormone-therapy/aromatase-inhibitors-anastrozole-exemestane-letrozole [Accessed 12 October 2020].
- Geisler J, Haynes B, Anker G, Dowsett M, Lønning PE. 2002. Influence of letrozole and anastrozole on total body aromatization and plasma estrogen levels in postmenopausal breast cancer patients evaluated in a randomized, cross-over study. J Clin Oncol. 20: 751-757.
- Miller WR, Jackson J. 2003. The therapeutic potential of aromatase inhibitors. Expert Opin Investig Drugs.12: 1-12.
- Early Breast Cancer Trialists’ Collaborative Group (EBCTCG). Aromatase Inhibitors Versus Tamoxifen In Early Breast Cancer: Patient-Level Meta-Analysis Of The Randomised Trials. 2015. Elsevier BV. Vol 386, no. 10001: 1341-1352.
- Oncotypeiq.com. 2020. About the Oncotype DX Breast Recurrence Score Test. [online] Available at: https://www.oncotypeiq.com/en-US/breast-cancer/healthcare-professionals/oncotype-dx-breast-recurrence-score/about-the-test
- National Institute for Health and Care Excellence (NICE). 2022. Abemaciclib with endocrine therapy for adjuvant treatment of hormone receptor-positive, HER2-negative, node-positive early breast cancer at high risk of recurrence. Technology appraisal guidance TA810. [online] Available at: https://www.nice.org.uk/guidance/ta810 [Accessed September 2026].
- National Institute for Health and Care Excellence (NICE). 2025. Ribociclib with an aromatase inhibitor for adjuvant treatment of hormone receptor-positive HER2-negative early breast cancer at high risk of recurrence. Technology appraisal guidance TA1086. [online] Available at: https://www.nice.org.uk/guidance/ta1086 [Accessed September 2026].
- National Institute for Health and Care Excellence (NICE). 2024. Tumour profiling tests to guide adjuvant chemotherapy decisions in early breast cancer (HTG719, previously DG58 and DG34). [online] Available at: https://www.nice.org.uk/guidance/htg719 [Accessed September 2026].
- Johnston S, Martin M, O’Shaughnessy J, et al. 2026. Overall survival with abemaciclib in early breast cancer. Ann Oncol. 2026 Feb;37(2):155-165 Available at: https://pubmed.ncbi.nlm.nih.gov/41110697/
- Johnston S, Harbeck N, Hegg R, Toi M, Martin M, Shao Z M , Zhang QY , Martinez Rodriguez JL, Campone M, Hamilton E, Sohn J, Guarneri V, Okada M, Boyle F, Neven P, Cortés J, Huober J, Wardley A, Tolaney SM, Cicin I, Smith IC, Frenzel M, Headley D, Wei R, San A, Belen and Hulstijn M, Cox J, O’Shaughnessy J, Rastogi P. (2020). Abemaciclib Combined With Endocrine Therapy for the Adjuvant Treatment of HR+, HER2−, Node-Positive, High-Risk, Early Breast Cancer (monarchE). Journal of Clinical Oncology.
- Cancer Research UK. Tamoxifen. [online] Available at: https://www.cancerresearchuk.org/about-cancer/treatment/drugs/tamoxifen [Accessed September 2026].
- Crown J, Stroyakovskii D, Yardley DA, et al. 2025. Adjuvant ribociclib plus nonsteroidal aromatase inhibitor therapy in patients with HR-positive/HER2-negative early breast cancer: 5-year follow-up of NATALEE efficacy outcomes and updated overall survival. ESMO Open. 10(11): 105858.
- Cancerresearchuk.org. 2020. Doxorubicin [online]. Available at: https://www.cancerresearchuk.org/about-cancer/cancer-in-general/treatment/cancer-drugs/drugs/doxorubicin [Accessed 12 October 2020]
- National Institute for Health and Care Excellence (NICE). 2023. Olaparib for adjuvant treatment of BRCA mutation-positive HER2-negative high-risk early breast cancer after chemotherapy. Technology appraisal guidance TA886. [online] Available at: https://www.nice.org.uk/guidance/ta886 [Accessed September 2026].
- Bardia A, Schmid P, Martín M, et al. 2026. Giredestrant vs standard-of-care endocrine therapy as adjuvant treatment for patients with estrogen receptor-positive, HER2-negative early breast cancer: results from the global phase III lidERA Breast Cancer trial (San Antonio Breast Cancer Symposium 2025, abstract GS1-10). Clinical Cancer Research. 32(4 Suppl): GS1-10.
- Hassett MJ, Somerfield MR, Baker ER, et al. 2020. Management of male breast cancer: ASCO guideline. Journal of Clinical Oncology. 38(16): 1849-1863.
- Pagani O, Walley BA, Fleming GF, et al. 2023. Adjuvant exemestane with ovarian suppression in premenopausal breast cancer: long-term follow-up of the combined TEXT and SOFT trials. Journal of Clinical Oncology. 41(7): 1376-1382.